Azoospermia means that a semen sample contains no sperm. People often call this condition zero sperm count. It can result from a blockage in the reproductive tract, reduced sperm production in the testes, hormonal problems, genetic conditions, or certain medical treatments. If you are looking for an azoospermia doctor in Surat, a proper evaluation should include more than one semen report. At Paaranu IVF, fertility care is led by Dr. Jayesh Patel, MD, D.G.O., Clinical Director & IVF Specialist, who has more than 25 years of experience in gynecology, fertility, and fetal medicine.
Finding zero sperm in a semen report does not automatically mean that biological fatherhood is impossible. The next step is to determine why sperm are absent and whether doctors can restore sperm production, correct a blockage, or retrieve sperm directly for IVF with ICSI.
What Is Azoospermia?
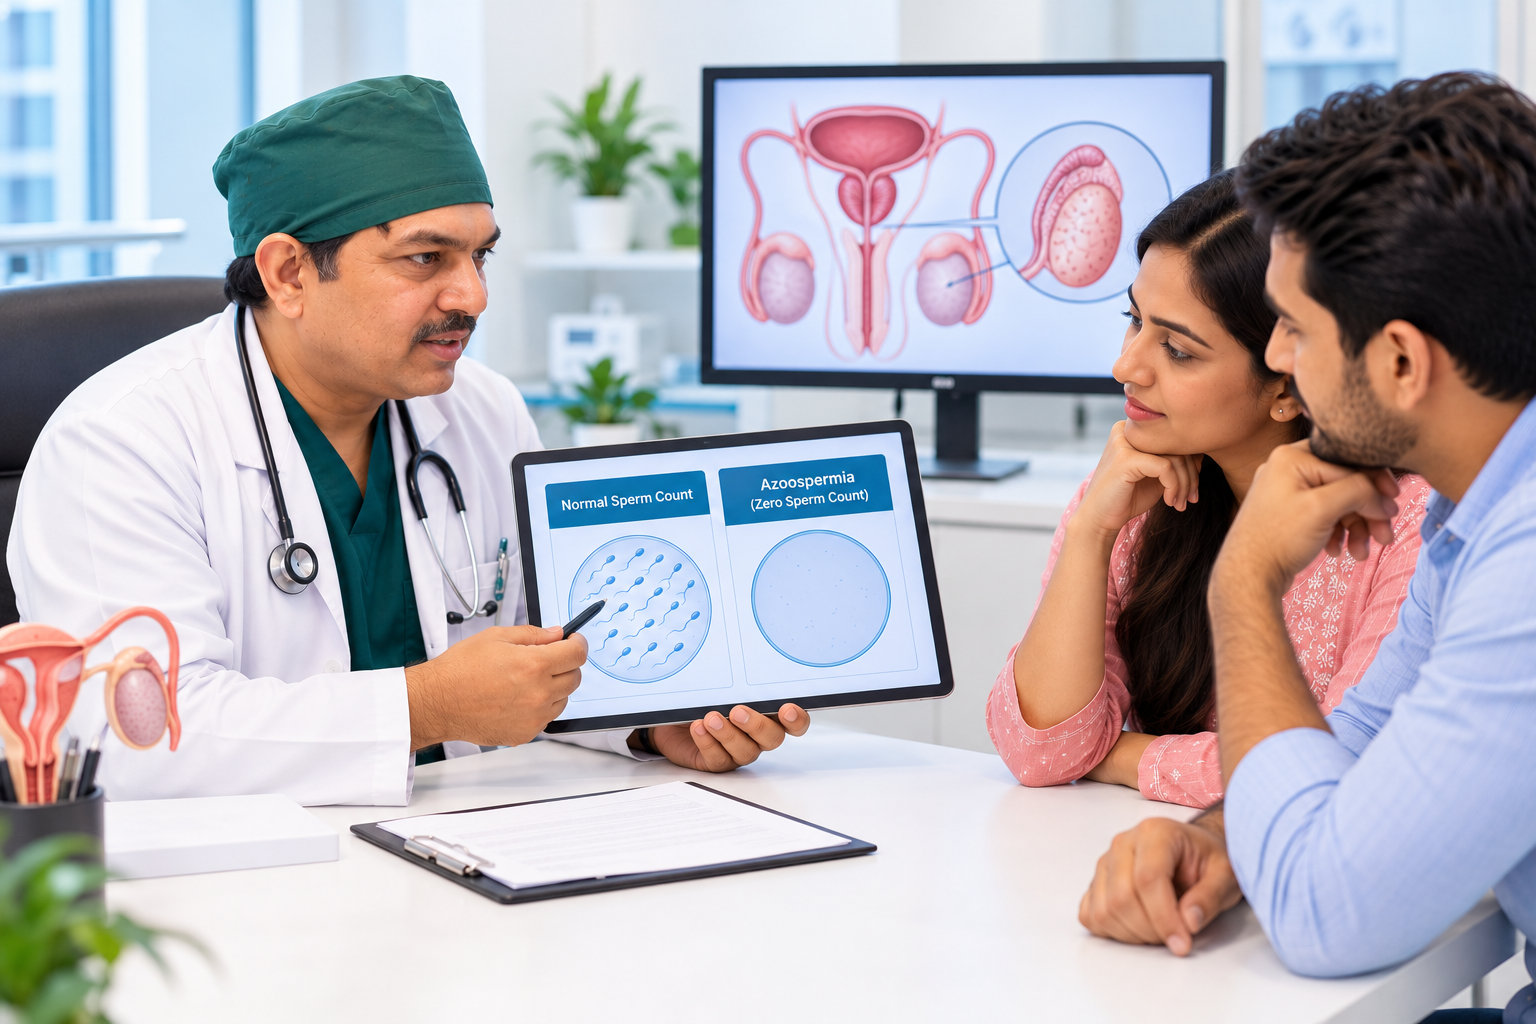
Azoospermia means doctors cannot find sperm in the ejaculate, including after laboratory examination of a centrifuged semen sample.
Doctors generally classify azoospermia into two major types:
- Obstructive azoospermia
- Non-obstructive azoospermia
Understanding which type a man has is important because treatment differs considerably.
What Is Obstructive Azoospermia?
Obstructive azoospermia occurs when the testes produce sperm, but a blockage prevents sperm from entering the semen.
Possible causes include:
- Blocked epididymis
- Blocked vas deferens
- Ejaculatory duct obstruction
- Previous vasectomy
- Previous infection or surgery
- Congenital absence of the vas deferens
In some cases, doctors can correct the blockage surgically. In other situations, they may retrieve sperm directly from the epididymis or testis and use it with ICSI. AUA/ASRM guidance recognises both reconstructive surgery and surgical sperm retrieval as treatment options for selected obstructive cases.
What Is Non-Obstructive Azoospermia?
Non-obstructive azoospermia, or NOA, occurs when the testes produce very little sperm or fail to produce enough sperm to appear in the ejaculate.
Possible causes include:
- Genetic abnormalities
- Testicular failure
- Hormonal disorders
- Previous chemotherapy
- Radiation therapy
- Undescended testes
- Severe testicular injury
- Certain infections
- Some medications
- Anabolic steroid use
Even when sperm do not appear in semen, small areas of sperm production may sometimes remain inside the testes.
What Causes Zero Sperm Count?
Azoospermia can develop for many different reasons.
Hormonal Problems
Hormones produced by the brain and pituitary gland help control sperm production.
Conditions involving FSH, LH, testosterone, or prolactin can affect fertility.
The AUA/ASRM guideline recommends hormonal evaluation including FSH and testosterone in men with azoospermia.
Genetic Conditions
Some men with azoospermia may have:
- Klinefelter syndrome
- Y-chromosome microdeletions
- CFTR-related abnormalities
- Other chromosomal problems
Doctors may recommend genetic testing in selected men, particularly when they suspect impaired sperm production.
Blockage in the Reproductive Tract
A blockage may prevent normally produced sperm from entering the semen.
Blockages may result from:
- Previous surgery
- Infection
- Vasectomy
- Congenital abnormalities
- Ejaculatory duct obstruction
Cancer Treatment
Chemotherapy and radiotherapy can damage sperm-producing cells.
Men who may receive fertility-threatening cancer treatment should ideally discuss sperm banking before treatment starts. AUA/ASRM guidance recommends fertility-preservation counselling before gonadotoxic treatment.
Testosterone and Anabolic Steroids
Taking external testosterone can suppress the hormones that stimulate sperm production.
AUA/ASRM guidance advises against testosterone monotherapy in men who want current or future fertility because it can suppress spermatogenesis.
What Are the Symptoms of Azoospermia?
Many men with azoospermia have no obvious symptoms.
They may only discover the condition after undergoing fertility testing.
Possible associated signs can include:
- Difficulty conceiving
- Small testes
- Reduced facial or body hair
- Low sexual desire
- Erectile problems
- Ejaculatory problems
- History of testicular surgery
- Previous chemotherapy or radiation
- Swelling or discomfort in the scrotum
However, a man can have normal sexual function and still have azoospermia.
How Is Azoospermia Diagnosed?
Diagnosis usually starts with semen analysis.
Doctors should not diagnose azoospermia from symptoms alone.
The evaluation may include:
- Repeat semen analysis
- Medical history
- Physical examination
- Hormonal blood tests
- Genetic tests
- Ultrasound in selected cases
- Assessment of semen volume
- Previous treatment or surgery history
AUA/ASRM guidance recommends using semen volume, physical examination, and FSH levels to help distinguish obstruction from impaired sperm production.
Is One Semen Analysis Enough to Diagnose Azoospermia?
Usually, doctors confirm the result carefully before making major treatment decisions.
Semen results can vary between samples.
The laboratory may centrifuge the semen and examine the pellet to look for very small numbers of sperm.
A true azoospermia diagnosis means the laboratory cannot detect sperm even after this careful examination.
Which Hormone Tests May Be Needed?
Doctors may check:
- FSH
- Testosterone
- LH
- Prolactin in selected cases
FSH can help the doctor understand whether the testes are receiving a strong signal to produce sperm.
For example, a high FSH level with small testes may suggest impaired sperm production, while normal testicular size and lower FSH may point more toward obstruction.
When Are Genetic Tests Needed for Azoospermia?
Doctors may recommend genetic evaluation when azoospermia appears to result from impaired sperm production.
Testing may include:
- Karyotype
- Y-chromosome microdeletion analysis
- CFTR testing in selected obstructive cases
AUA/ASRM guidance recommends karyotype and Y-chromosome microdeletion testing in men with primary infertility and azoospermia when clinical findings suggest impaired sperm production.
Genetic testing can also help guide counselling before fertility treatment.
Does Azoospermia Mean a Man Is Sterile?
Not always.
Azoospermia means sperm do not appear in the ejaculate. It does not necessarily mean the testes contain no sperm at all.
Some men with obstructive azoospermia produce sperm normally but cannot release it because of a blockage.
Some men with non-obstructive azoospermia may still have small areas of sperm production inside the testes.
This is why proper assessment by an experienced fertility specialist matters.
Can Azoospermia Be Treated?
Yes, treatment options exist for many men.
The correct approach depends on the cause.
Possible treatments include:
- Hormonal treatment
- Correction of an obstruction
- Surgical sperm retrieval
- IVF with ICSI
- Fertility preservation
- Donor sperm in selected situations
Not every patient needs the same treatment.
Can Hormonal Treatment Help Azoospermia?
It can help when doctors identify a specific hormone disorder.
For example, men with hypogonadotropic hypogonadism may respond to fertility-directed hormonal treatment.
However, routine medication does not restore sperm production in every case of non-obstructive azoospermia.
AUA/ASRM guidance notes that evidence for hormonal manipulation before surgical sperm retrieval in NOA remains limited.
Patients should avoid self-medicating with testosterone or fertility supplements.
Can Surgery Treat Obstructive Azoospermia?
Sometimes.
Doctors may consider microsurgical reconstruction when a correctable blockage prevents sperm from entering the semen.
Possible procedures depend on the location of obstruction.
In selected men, reconstruction may restore sperm to the ejaculate.
When reconstruction is not suitable, surgical sperm retrieval followed by IVF with ICSI may offer another route to conception.
What Is Surgical Sperm Retrieval?
Surgical sperm retrieval involves collecting sperm directly from the epididymis or testis.
Techniques may include:
- PESA
- TESA
- TESE
- Micro-TESE
The appropriate method depends on whether azoospermia is obstructive or non-obstructive.
Paaranu IVF includes TESA, PESA, and TESE among its fertility treatment options.
What Is PESA?
PESA stands for Percutaneous Epididymal Sperm Aspiration.
A doctor uses a needle to retrieve sperm from the epididymis.
Doctors may use PESA in selected cases of obstructive azoospermia when sperm production remains intact.
What Is TESA?
TESA stands for Testicular Sperm Aspiration.
The doctor uses a needle to obtain tissue or sperm directly from the testis.
Embryologists then examine the sample for viable sperm.
What Is TESE?
TESE stands for Testicular Sperm Extraction.
During TESE, the doctor removes a small amount of testicular tissue, and the laboratory searches the tissue for sperm.
Doctors may use TESE in selected obstructive and non-obstructive cases.
What Is Micro-TESE?
Micro-TESE stands for Microdissection Testicular Sperm Extraction.
During micro-TESE, a surgeon examines testicular tissue under magnification to identify areas more likely to contain sperm.
AUA/ASRM guidance supports micro-TESE as an important sperm-retrieval technique for men with non-obstructive azoospermia.
However, micro-TESE cannot guarantee sperm retrieval.
Can Retrieved Sperm Be Used for ICSI?
Yes.
If the fertility team retrieves viable sperm, embryologists may use it with ICSI.
During ICSI, an embryologist injects a single selected sperm directly into an egg.
This approach can help when sperm numbers are extremely low or when doctors obtain sperm surgically.
Paaranu IVF provides ICSI treatment in Surat for male-factor infertility, including certain cases of obstructive azoospermia.
What Is the Difference Between IVF and ICSI for Azoospermia?
Conventional IVF places sperm and eggs together in the laboratory and allows fertilisation to occur without directly injecting sperm.
ICSI differs because the embryologist injects one sperm directly into an egg.
In azoospermia cases where doctors retrieve only a small number of sperm surgically, ICSI usually plays a more important role.
Learn more about IVF treatment in Surat and other fertility options available at Paaranu IVF.
What Happens if Doctors Cannot Retrieve Sperm?
Unfortunately, sperm retrieval does not succeed in every patient.
If doctors cannot find viable sperm, the fertility team may discuss:
- Reviewing the diagnosis
- Additional specialist assessment
- Genetic counselling
- Future treatment options
- Donor sperm treatment where medically and legally appropriate
The next step depends on the couple’s medical situation and treatment goals.
Can Donor Sperm Be Used When Azoospermia Treatment Does Not Work?
Yes, donor sperm may become an option in selected situations.
For example, couples may consider donor sperm if sperm retrieval fails or if using the male partner’s sperm is not medically appropriate.
Paaranu IVF also provides information about donor sperm IUI in Surat.
Treatment with donor sperm should follow applicable ART regulations and appropriate counselling.
Can Azoospermia Affect Overall Health?
Sometimes.
Azoospermia can reflect underlying conditions involving:
- Hormonal health
- Testicular function
- Genetic abnormalities
- Previous cancer treatment
- Congenital reproductive tract problems
For this reason, an azoospermia evaluation should not focus only on fertility.
The doctor should also assess whether an underlying medical problem requires treatment or long-term follow-up.
Can Lifestyle Changes Cure Zero Sperm Count?
Lifestyle changes support general reproductive health, but they cannot correct every cause of azoospermia.
Healthy habits may include:
- Avoiding smoking
- Limiting alcohol
- Avoiding recreational drugs
- Avoiding anabolic steroids
- Maintaining a healthy weight
- Managing chronic illnesses
- Reviewing fertility-harming medicines with a doctor
However, a blockage, genetic condition, or severe testicular sperm-production problem usually requires medical evaluation beyond lifestyle changes.
Should Men With Azoospermia Take Testosterone?
Men trying to conceive should not take testosterone without specialist advice.
External testosterone can suppress LH and FSH signals and reduce or completely stop sperm production.
AUA/ASRM guidance specifically advises against testosterone monotherapy in men interested in current or future fertility.
If testosterone levels are low, an azoospermia doctor should first identify the cause and discuss fertility-preserving treatment options.
When Should You See an Azoospermia Doctor?
Consult an azoospermia doctor if:
- A semen analysis shows zero sperm
- Repeat testing confirms azoospermia
- You have a history of testicular surgery
- You underwent chemotherapy or radiotherapy
- You have very small testes
- You have hormonal symptoms
- You had a vasectomy
- You have a genetic fertility condition
- You and your partner cannot conceive
Early evaluation helps determine whether doctors can correct the cause or retrieve sperm for assisted reproduction.
Why Consult Paaranu IVF for Azoospermia in Surat?
Paaranu IVF provides fertility evaluation and treatment for azoospermia and other male-factor infertility conditions.
The clinic’s treatment services include surgical sperm retrieval procedures such as TESA, PESA, and TESE, along with IVF and ICSI.
Care is led by Dr. Jayesh Patel, MD, D.G.O., Clinical Director & IVF Specialist, who has more than 25 years of experience in gynecology, fertility, and fetal medicine. His areas of expertise include male infertility and azoospermia.
Patients can also explore Paaranu IVF’s fertility specialists in Surat for further information about specialist care.
What Should You Ask Your Azoospermia Doctor?
Before starting treatment, consider asking:
- Is my azoospermia obstructive or non-obstructive?
- Should I repeat my semen analysis?
- Do I need hormone tests?
- Do I need genetic testing?
- Could a blockage be causing the problem?
- Can medicines help in my case?
- Do I need sperm retrieval?
- Which technique is most suitable for me?
- What are the chances of finding sperm?
- Would ICSI be required?
- Should my partner undergo fertility testing at the same time?
A clear diagnosis should come before choosing a treatment.
Can Men With Azoospermia Become Biological Fathers?
Some can.
If doctors find sperm in the reproductive tract or testes, they may retrieve it and use it with ICSI.
Other men may benefit from treatment of an obstruction or hormonal problem.
However, outcomes differ significantly depending on the cause of azoospermia. No treatment can guarantee sperm retrieval, fertilisation, pregnancy, or live birth.
The most important first step is to determine the exact cause with an experienced azoospermia doctor.
Frequently Asked Questions
Is zero sperm count permanent?
Not always. Some causes are potentially reversible, while others may require surgical sperm retrieval or assisted reproduction. The outcome depends on the underlying cause.
Can azoospermia be cured naturally?
Lifestyle improvements may support reproductive health, but they cannot reliably treat structural blockages, major genetic conditions, or severe testicular failure.
Can a man with azoospermia have a baby?
Yes, some men with azoospermia can achieve biological fatherhood through treatment, surgical sperm retrieval, and ICSI. Success depends on whether viable sperm are available and on the female partner’s fertility factors.
Is azoospermia the same as low sperm count?
No. Low sperm count means sperm are present but fewer than expected. Azoospermia means no sperm are detected in the ejaculate after appropriate laboratory examination.
Can azoospermia improve with medicines?
Medicines can help when a treatable hormonal disorder causes azoospermia. They do not work for every type of azoospermia.
Which test confirms azoospermia?
Semen analysis confirms the absence of sperm. The laboratory may centrifuge the sample and examine the pellet carefully before confirming the diagnosis.
Is ICSI needed in azoospermia?
When doctors surgically retrieve only a small number of sperm, ICSI commonly allows an embryologist to inject a single sperm directly into an egg.
Does micro-TESE guarantee sperm retrieval?
No. Micro-TESE can improve the ability to search for sperm in selected non-obstructive cases, but it cannot guarantee that viable sperm will be found.
Should both partners undergo fertility evaluation?
Yes. Male and female fertility factors can occur together. The AUA/ASRM guideline supports evaluating both partners during infertility assessment.